

Introduction
Global population aging has become a critical demographic trend with profound societal impacts worldwide. According to a global decomposition analysis, population aging was associated with an increase of 12 million deaths worldwide between 1990 and 2017, highlighting the severity of the aging crisis. This demographic shift is particularly evident in China, where population aging has reached unprecedented levels [1]. In China, the aging population is particularly notable for its immense scale, rapid expansion, pronounced regional disparities, and the significant challenges it poses. By the close of 2023, the number of elderly individuals aged 60 and over in China is expected to reach 297 million, representing 21.1% of the total population. Looking ahead, it is projected that by 2035, this number will surpass 400 million, accounting for approximately 30% of the population, thereby placing China on the precipice of a severe aging crisis [2]. The swift expansion of the elderly demographic has heightened concerns regarding the societal impacts of aging. Older adults are particularly susceptible to a range of diseases due to natural physiological decline [3] and reduced immunity [4]. For instance, some studies predict that, driven by the aging population, the incidence of cardiovascular diseases will increase by 90.0% between 2025 and 2050 [5, 6]. The economic burden of age-related diseases exerts considerable financial pressure, particularly on developing nations, where it can stymie economic growth and undermine efforts to establish sustainable social systems [7]. Addressing these challenges requires developing and implementing proactive policies to improve the health and well-being of the aging population.
Air pollution substantially challenges sustainable development, impacting ecosystems, economic stability, and public well-being. Among its many adverse effects, it is particularly harmful to human health, with older adults being especially vulnerable. Existing studies indicate that exposure to air pollutants can lead to acute health issues in the short term, such as respiratory irritation [8], coughing [9], and shortness of breath [10], as well as an increased risk of stroke [11]. Over the long term, air pollution is associated with the development of chronic respiratory diseases, including asthma [12], chronic obstructive pulmonary disease (COPD) [13], and lung cancer [14]. For instance, Han et al. found that a 10 μg/m³ increase in PM2.5 concentration correlates with a 7% increase in mortality risk among middle-aged and elderly individuals [15]. Furthermore, long-term exposure to air pollutants has been shown to adversely affect daily living activities and cognitive function, particularly in middle-aged and older adults with existing comorbidities [16]. Schikowski et al. highlighted that increasing long-term air pollution exposure may contribute to a rising burden of cognitive decline in older adults [17]. Air pollutants can trigger inflammatory responses in the brain, leading to blood-brain barrier dysfunction, neurodegeneration, apoptosis, and cerebrovascular lesions, which are strongly linked to an increased risk of developing chronic inflammatory demyelinating polyneuropathy (CIDP) and Alzheimer’s disease in older populations [18].
In response to the pressing need to improve air quality and enhance the well-being of its residents, China has prioritized air pollution control. The Law of the People’s Republic of China on Prevention and Control of Air Pollution has undergone several revisions since its initial enactment in 1987. This legislation outlines the fundamental principles of air pollution prevention and control, as well as the supervision and management systems, preventive measures, and legal responsibilities. The Chinese government has also implemented desulfurization, denitrification, and dedusting renovation projects targeting key industrial sectors, such as iron and steel, cement, and electric power, to mitigate emissions of sulfur dioxide, nitrogen oxides, and particulate matter [19]. China has implemented key national policies like the Air Pollution Prevention and Control Action Plan (2013) and the Three-Year Action Plan for Winning the Blue Sky Defense Battle (2018) to combat air pollution. These initiatives target major regions such as Beijing-Tianjin-Hebei and the Yangtze River Delta, introducing stricter emission standards, promoting industrial upgrades, and advancing clean energy adoption. The government has also strengthened environmental monitoring and enforcement, ensuring regulatory compliance and accountability among polluters. Previous research has significantly contributed to understanding environmental regulation and its impact on public health. Environmental regulation serves as a crucial tool for environmental governance, aimed at constraining economic agents’ emissions and addressing the externalities of environmental pollution. Studies have demonstrated [20-22] that the strength of environmental regulation is a critical factor influencing green innovation within enterprises [21]. Appropriate levels of environmental regulation can stimulate technological innovation [22], drive improvements in production methods, and enhance the level of green innovation in pollution-intensive industries [23]. Wang et al. [24] and Cheng et al. [25] respectively demonstrated from the perspectives of external environmental constraints and central environmental inspections that environmental regulation can significantly enhance firms’ green technological innovation. Green innovation has environmental spillover effects [26], with most of its benefits manifesting as public goods [27]. It contributes to mitigating environmental pollution and reducing harm to human health [28, 29]. Additionally, initiatives such as central environmental protection inspections and targeted air pollution prevention and control plans have proven effective in reducing carbon emissions, alleviating air pollution, and improving overall air quality [20].
Moreover, environmental pollution—encompassing air, water, and noise—can severely affect residents’ health [30]. In the context of universal health care, scholars have increasingly recognized the link between environmental regulation and public health. Some researchers argue that air pollution control policies can lower the incidence of respiratory and cardiovascular diseases by reducing the concentration of hazardous chemicals in the air, thereby improving residents’ health and decreasing associated healthcare costs [31, 32]. Furthermore, effective noise management interventions are vital for addressing sleep disorders, mood disturbances, cognitive impairments, and cardiovascular diseases among the elderly [33]. While existing studies have explored the positive effects of environmental regulation on the health of older adults, they often overlook the adverse consequences of pollution transfer. Although local air quality in China has improved, pollution transfer remains a significant issue. The migration of pollution from economically developed regions to disadvantaged areas, as well as from urban to rural settings, highlights the shortcomings of the territorial management model of environmental governance [34]. The trans-regional and spatial dispersion of air pollution cannot be confined to fixed areas, presenting challenges that the current territorial environmental governance model struggles to address [35]. Air pollution not only jeopardizes the health of local populations but also adversely affects the health of individuals in other regions due to pollution transfer. Dedoussi et al. found that 41% to 53% of premature deaths in the U.S. were linked to interstate air pollution transfer [36], while Zhao et al. reported similar findings in China [37]. The negative health impacts of pollution transfer are particularly pronounced among older age groups [38]. Long-term exposure to combustion-related fine particulate matter (PM2.5) and sulfur oxide-related air pollution is a significant environmental risk factor, with each 10 µg/ m³ increase in PM2.5 associated with approximately 4%, 6%, and 8% higher risks of all-cause, cardiopulmonary, and lung cancer mortality, respectively [39]. Therefore, this study concludes that addressing cross-regional air pollution challenges necessitates cooperation among governments to establish collaborative mechanisms for regional air pollution prevention and control, ultimately improving air quality and safeguarding residents’ health. Recent studies highlight that while local environmental regulations improve air quality, they often exacerbate interregional pollution transfer due to industrial shifts [40]. Disparities in governance capacity further amplify health inequities, with underdeveloped areas disproportionately affected by pollution spillovers from urban centers [41]. These findings underscore the limitations of territorially bound governance and the need for integrated regional strategies. Consequently, investigating the health effects of regional air pollution prevention and control mechanisms is a topic of significant importance.
This study first utilizes foundational theories to examine how regional air pollution cooperative governance can serve as a practical solution to address these challenges, particularly in safeguarding the health of vulnerable groups such as the elderly.
This study’s theoretical foundation is primarily based on externality theory [42], intergovernmental cooperative governance theory [43], and environmental health theory [44]. These theories provide a robust framework for understanding how regional air pollution cooperative governance policies can improve air quality and, consequently, promote the health of the elderly.
First, externality theory states that certain economic activities impose costs or benefits on third parties that are not reflected in market prices [42]. Air pollution, as a typical negative externality, entails social costs exceeding the private costs of polluters. Given its cross-border transmission nature, individual local governments may lack sufficient incentives to address pollution, as the benefits of improved air quality often spill over to neighboring regions [45]. This results in suboptimal environmental quality and sustained health risks [46]. Second, intergovernmental cooperative governance theory emphasizes the importance of collaboration among different levels of government to address issues that transcend administrative boundaries [43, 47]. Air pollution exhibits a cross-regional nature, necessitating coordinated policies and joint actions among governments [48]. Collaborative governance frameworks facilitate resource sharing, policy coordination, and collective action, thereby enhancing the effectiveness of environmental interventions [49]. Third, environmental health theory focuses on the impact of environmental factors on human health, particularly the effects of air pollution on respiratory diseases [44]. This theory posits that reducing exposure to environmental pollutants can significantly decrease the incidence of diseases and improve population health [50]. Studies have shown that air pollution is closely linked to various respiratory diseases, with an especially profound impact on the elderly [51].
Based on the above theories, regional air pollution cooperative governance policies can affect the health of the elderly through the following mechanisms:
First, cooperative governance policies reduce the negative externalities of air pollution. Regional cooperation enables the implementation of stricter and more uniform emission standards, as well as joint monitoring and enforcement activities, which significantly reduce pollutant emissions [52]. Research shows that after implementing cooperative governance policies, concentrations of key pollutants such as PM2.5, NOx, and SO2 have significantly declined [53]. These pollutants are major contributors to respiratory diseases, and their reduction directly decreases the incidence of pulmonary diseases and asthma among the elderly [54].
Second, cooperative governance enhances resource efficiency and policy effectiveness. By integrating regional resources and expertise, governments can develop and implement more comprehensive air quality management strategies [55]. This collective action overcomes the limitations of fragmented local policies and leverages economies of scale in pollution control measures [56]. Improvements in air quality have a significant positive impact on the health of the elderly [51].
Third, cooperative governance generates positive health spillover effects. Implementing regional policies expands the scope of health benefits beyond individual jurisdictions [57]. The elderly, whose mobility is often limited, are more affected by local environmental conditions. Overall improvements in regional air quality have a significant positive impact on their health outcomes [58].
Based on the above theoretical analysis, the study proposes the hypothesis as follows:
H1: Regional air pollution cooperative governance policies help improve the health of the elderly by enhancing air quality.
This hypothesis serves as a cornerstone for the analysis presented in this study. By examining empirical data, this research aims to provide evidence of the effectiveness of regional air pollution cooperative governance in improving air quality and its subsequent health benefits for elderly populations. The findings will contribute to the broader understanding of how policy interventions can address public health concerns in the face of environmental challenges.
Leveraging multi-period data from the China Health and Retirement Longitudinal Study (CHARLS), this paper employs a Difference-in-Differences (DID) modeling to analyze the impacts of regional air pollution synergistic management policies on the health of the elderly, as well as the mechanisms underlying these impacts. This study aims to introduce several innovative elements. Firstly, while numerous studies have examined the positive significance of environmental policies in promoting the health of the elderly, they often neglect the implications of pollution transfer. This paper utilizes a quasi-natural experiment, specifically the subregional implementation of China’s air pollution joint prevention and control policies, to investigate the effects of regional air pollution prevention and control collaborative mechanisms on elderly health. Secondly, whereas existing research tends to adopt a macro perspective in exploring the positive implications of environmental policies, this study employs data from the CHARLS survey, facilitating a micro-examination of elderly health. This micro perspective is relatively rare in the current literature, particularly in analyses of the impact of environmental regulation on older adults’ health. Building on this micro-level focus, this study employs a Difference-in-Differences (DID) approach within a quasi-natural experimental framework, using longitudinal CHARLS data to assess the causal impacts of regional air pollution governance on elderly health. A key methodological advancement lies in addressing pollution transfer effects and uncovering mechanisms like air quality improvement and reduced respiratory illnesses. This nuanced approach provides a fresh perspective and enriches existing policy impact analysis research.
The remainder of this paper is organized as follows: the following Section delves into the data sources, the construction of variables, and the modeling approaches utilized. “Results” Section offers an extensive presentation of the empirical findings. In “Discussion” Section, a thorough discussion is undertaken concerning the regression outcomes and the heterogeneity analysis. Finally, “Conclusions” Section encapsulates the main conclusions and puts forward policy recommendations.
Materials and Methods
Data Sources
This study utilizes two primary data sources to ensure comprehensive and reliable analysis.
The first source is the China Health and Retirement Longitudinal Study (CHARLS), an interdisciplinary survey project initiated by the Institute of National Studies at Peking University and executed by the China Social Science Research Center. CHARLS employs a multistage random sampling method, covering 150 counties and 450 communities across China. Within each household, individuals aged 45 and older were randomly selected as primary respondents, with data collected on their basic information, health status, and healthcare utilization. Since its inception in 2011, CHARLS has conducted multiple waves of longitudinal data collection (2013, 2015, 2018, and 2020), providing a rich dataset that captures nearly a decade of health-related trends and temporal changes for older adults. The longitudinal nature of the dataset is particularly valuable for this study, enabling the examination of dynamic health impacts over time within a Difference-in-Differences (DID) framework. This approach enhances causal inference by controlling for unobserved individual heterogeneity and temporal confounders, ensuring that observed effects can be robustly attributed to air pollution prevention policies.
The second source is the China Regional Statistical Yearbook, an annual publication compiled by the National Bureau of Statistics. This yearbook offers comprehensive data on the economic and social development of various regions in China, providing the regional variables essential for contextual analysis.
The integration of these datasets strengthens the analysis. CHARLS provides granular, individual-level health data with precise temporal markers, making it well-suited for evaluating policy impacts on health outcomes. Meanwhile, the regional statistics from the yearbook offer critical contextual insights, enabling nuanced and policy-relevant conclusions. Together, these data sources enhance the study’s robustness and reliability.
The CHARLS study was approved by the Biomedical Ethics Review Committee of Peking University (approval number IRB00001052–11015), and all participants provided informed consent.
Table 1.
Indexes of mental health status.
Variable Construction
Explained Variable - Health Status of the Elderly
The health status of the elderly is assessed through two key dimensions: physiological health and mental health. Physiological health is assessed using indicators for acute and chronic diseases, as well as self-reported health scores. Acute diseases considered in this analysis include heart disease, stroke, and cancer, with each condition being assigned a score of 1, leading to a cumulative score range of the closed interval, including 0 and 3. Chronic diseases include conditions such as chronic lung disease, asthma, hypertension, dyslipidemia, diabetes, liver disease, kidney disease, gastric disease, and arthritis. Each condition is scored as 1, resulting in a total possible score range of the closed interval, including 0 and 9. Self-assessed health scores (Shealth) were derived from responses to the survey question, “How healthy do you think you are?” Respondents who selected “very bad” are assigned a score of 1, “bad” a score of 2, “fair” a score of 3, and “good” a score of 4. Mental health is measured using two sub-indicators: cognitive function scores and self-reported depression levels. In this study, the entropy method is employed to calculate secondary indicators based on their combined scores, attributes, and weights, which are informed by existing research [59]. The attributes and definitions of both the primary and secondary indicators and the weights assigned to these secondary indicators are detailed in Table 1.
Core Explanatory Variables - Coordinated Regional Air Pollution Prevention and Control
The core explanatory variable (CEV) captures the implementation of regional air pollution prevention and control policies through a dummy variable. This variable indicates whether a specific region implemented these measures starting in 2012, based on the Twelfth Five-Year Plan for the Prevention and Control of Air Pollution in Priority Regions. Regions where the policies were applied are coded as “1” and others as “0”. Serving as an interaction term in the Difference-in-Differences (DID) model, this classification clearly distinguishes treatment and control groups, facilitating the assessment of policy impacts.
The selection of this variable is both policy-relevant and theoretically grounded. The Twelfth Five-Year Plan highlighted the importance of regional coordination to address air pollution, a necessity reinforced by studies showing significant reductions in PM2.5 levels and health improvements in affected areas [39, 52]. From a theoretical perspective, air pollution represents a negative externality with cross-regional transmission. Collaborative governance and externality theories suggest that joint regional efforts can mitigate pollution spillovers, reduce social costs, and improve policy efficiency [42, 49].
To ensure the robustness and validity of this variable, the study employs parallel trend tests, placebo tests, and Propensity Score Matching (PSM-DID). These methods address selection bias and confirm the variable’s ability to capture the policy’s true effects [60, 61]. Heterogeneity analyses further reveal stronger effects in rural areas and among high-income groups, while urban areas and low-income populations experience more limited benefits. These findings validate the variable’s design and offer actionable insights for refining future policies [62].
In sum, the CEV is carefully constructed to align with both theoretical and practical considerations. Its validity is supported by rigorous methodologies, making it an effective tool for evaluating the health impacts of coordinated air pollution prevention and control policies.
Control Variables
The control variables in this study include demographic characteristics of older adults, health-related behaviors, and regional variables. Demographic characteristics of the elderly encompass age (age), gender (gender), education level (edu), marital status (marry), and economic income (income). As individuals age, they typically experience a gradual decline in physical functions, reduced immunity, and an increased risk of diseases [63]. Hence, age emerges as a critical factor influencing the health of the elderly. Furthermore, significant gender differences exist in health status and disease risk. For example, even when exposed to identical risk factors, men and women may experience different health outcomes [64]. A higher education level is generally associated with better health literacy and healthier behaviors, which can enhance disease prevention capabilities [65]. Marital status is categorized as married, unmarried, divorced, or widowed. Studies have indicated that married older adults often benefit from superior social support and better mental health [66]. Additionally, higher economic income is frequently linked to improved living conditions and greater access to medical care, both of which positively impact the health of older adults [67]. Health-related behaviors included smoking status and alcohol consumption. Numerous studies have identified smoking and drinking as significant risk factors for a range of diseases, such as chronic lung disease, hypertension, and liver cirrhosis, all of which are inversely correlated with overall health [68].
Table 2.
Descriptive statistics for each of the main variables.
Regional variables encompass regional gross domestic product (GDP), the proportion of the secondary sector, and the logarithm of the number of licensed healthcare professionals per 10,000 individuals (Ln Number of doctors and nurses). A higher GDP typically signifies a prosperous regional economy, which can provide enhanced public services and healthcare resources, thereby contributing to the health of older adults [69]. Conversely, regions with a high concentration of secondary industries may experience elevated levels of air pollution, which could adversely affect the health of the elderly [70]. A higher ratio of healthcare professionals generally indicates a more robust primary healthcare system and better accessibility to healthcare services, both of which are strongly associated with positive health outcomes for older adults [71].
This study controls for both regional fixed effects and year fixed effects. The coefficients derived from the analysis measure the impact of air pollution control policies, reflecting their net effect on the health of the elderly.
This study incorporates both regional and year fixed effects to ensure a robust analysis, with the resulting coefficients effectively isolating the impact of air pollution control policies. These coefficients represent the net effect of these interventions on the health outcomes of the elderly population. A comprehensive summary of the dataset’s descriptive statistics, which highlights the key variables under consideration, is presented in Table 2.
Empirical Model
The Difference-in-Differences (DID) model is a widely recognized method for policy evaluation. It is valued for its ability to estimate causal effects by comparing changes over time between intervention and control groups. In this study, the adoption of air pollution control measures provides a quasi-natural experimental setting, making the DID model particularly suitable for analyzing their impacts.
A key strength of the DID model lies in its ability to combine “before-and-after” and “intervention-versus-control” differences, effectively mitigating the influence of confounding factors. By incorporating covariates that capture individual and contextual characteristics, the model further reduces potential biases, improving the precision of policy effect estimates. This approach also addresses the non-random nature of sample allocation inherent in natural experiments.
Table 3.
Benchmark regression results.
Moreover, the DID model is effective in controlling for unobserved time-invariant factors [72] and is robust against confounding trends when temporal and regional fixed effects are included, as demonstrated by Greenstone and Hanna (2014) [73]. It is particularly well-suited for capturing inter-regional spillover effects, which are crucial in air pollution studies due to the transfer of pollutants across regions [36].
This study leverages longitudinal data from the China Health and Retirement Longitudinal Study (CHARLS), enhancing the analysis’ robustness. The rich temporal and individual-level data allow for a nuanced evaluation of policy impacts, consistent with findings from Zhang et al. [74] and Zhang et al. (2022) [75].
In summary, the DID model is employed to rigorously assess the impact of air pollution control measures on older adults’ health outcomes, aligning with the research’s theoretical framework and the quasi-experimental nature. The model is specified as follows:
Shealthit = α0+ α1DIDit+γi+μt+εit
In this model, Shealth is used to measure the health status of the older adult, with subscript i denoting the older adult and t denoting the year.
The DID variable serves as the core explanatory variable; if the elderly individual’s place of residence has implemented the air pollution prevention policy in year t, the DID variable is assigned a value of “1”; otherwise, it is assigned a value of “0”. This variable is equivalent to the interaction term in a traditional double-differential approach, with Controlit denoting control variables for a range of personal characteristics and social circumstances of rural older adults, γi being a regional fixed effect, and μt being a yearly fixed effect.
Heterogeneity Testing Methods
This study adopts a structured approach to analyzing the heterogeneous impacts of air pollution control policies. The analysis integrates subgroup regressions, interaction term analysis, and robustness checks. These methods were carefully chosen to address potential challenges and ensure the reliability of the findings.
Subgroup regressions divide the sample based on key characteristics such as rural versus urban residence, income levels, and digital infrastructure. This segmentation helps uncover variations in policy effects across different contexts. For instance, analyzing rural and urban groups separately reveals spatial differences, while stratification by income and technological factors highlights disparities driven by economic and infrastructural conditions. This approach aligns closely with the study’s objective of understanding how policy impacts vary across demographic and regional subpopulations, providing actionable insights for targeted policy improvements.
Interaction term analysis is incorporated into the DID model to capture moderating effects. This method quantifies differential impacts under varying conditions by interacting the policy variable with subgroup characteristics, such as income levels and digital infrastructure indices. This is particularly suitable for addressing the study’s core research question: how contextual factors influence the effectiveness of air pollution control policies.
Robustness checks enhance the validity of the findings. The Propensity Score Matching-Difference-in-Differences (PSM-DID) method mitigates selection bias and ensures comparability between treatment and control groups based on observed characteristics. This is critical for addressing the quasi-experimental nature of the policy intervention, bolstering the causal inference of the results. Placebo tests further confirm that the observed effects are not attributable to random factors or unrelated variables, strengthening the credibility of the heterogeneity findings.
To aid interpretation, visualization tools such as forest plots display effect sizes and confidence intervals for each subgroup, facilitating clear comparisons across contexts. This comprehensive analytical framework not only ensures the robustness and reliability of the results but also provides practical insights for designing policies tailored to diverse populations and regions.
Results
Basic Regression Results
This study examines the effects of air pollution control policies on the health outcomes of elderly individuals. The basic regression outcomes are meticulously detailed in Table 3. In Column (1) of Table 3, the estimation results indicate that, without including any control variables, the DID model exhibits a significantly positive value at the 5% level, with a regression coefficient of 0.0222. This finding implies that air pollution control policies have exerted a beneficial influence on the health of elderly individuals. Including demographic and regional variables in Column (2) enhances the comprehensiveness of the analysis. The demographic variables encompass factors such as age, education level, marital status, gender, income, smoking habits, and alcohol consumption among the elderly, while the regional variables include GDP, the share of the secondary industry, and the logarithm of the number of licensed healthcare professionals per 10,000 people. The regression results demonstrate that, although the DID coefficient maintains its significant negative status at the 5% level, the model’s overall goodness of fit improves. This enhancement in fit further bolsters the stability and robustness of the benchmark regression.
Effectiveness of Air Pollution prevention and Control
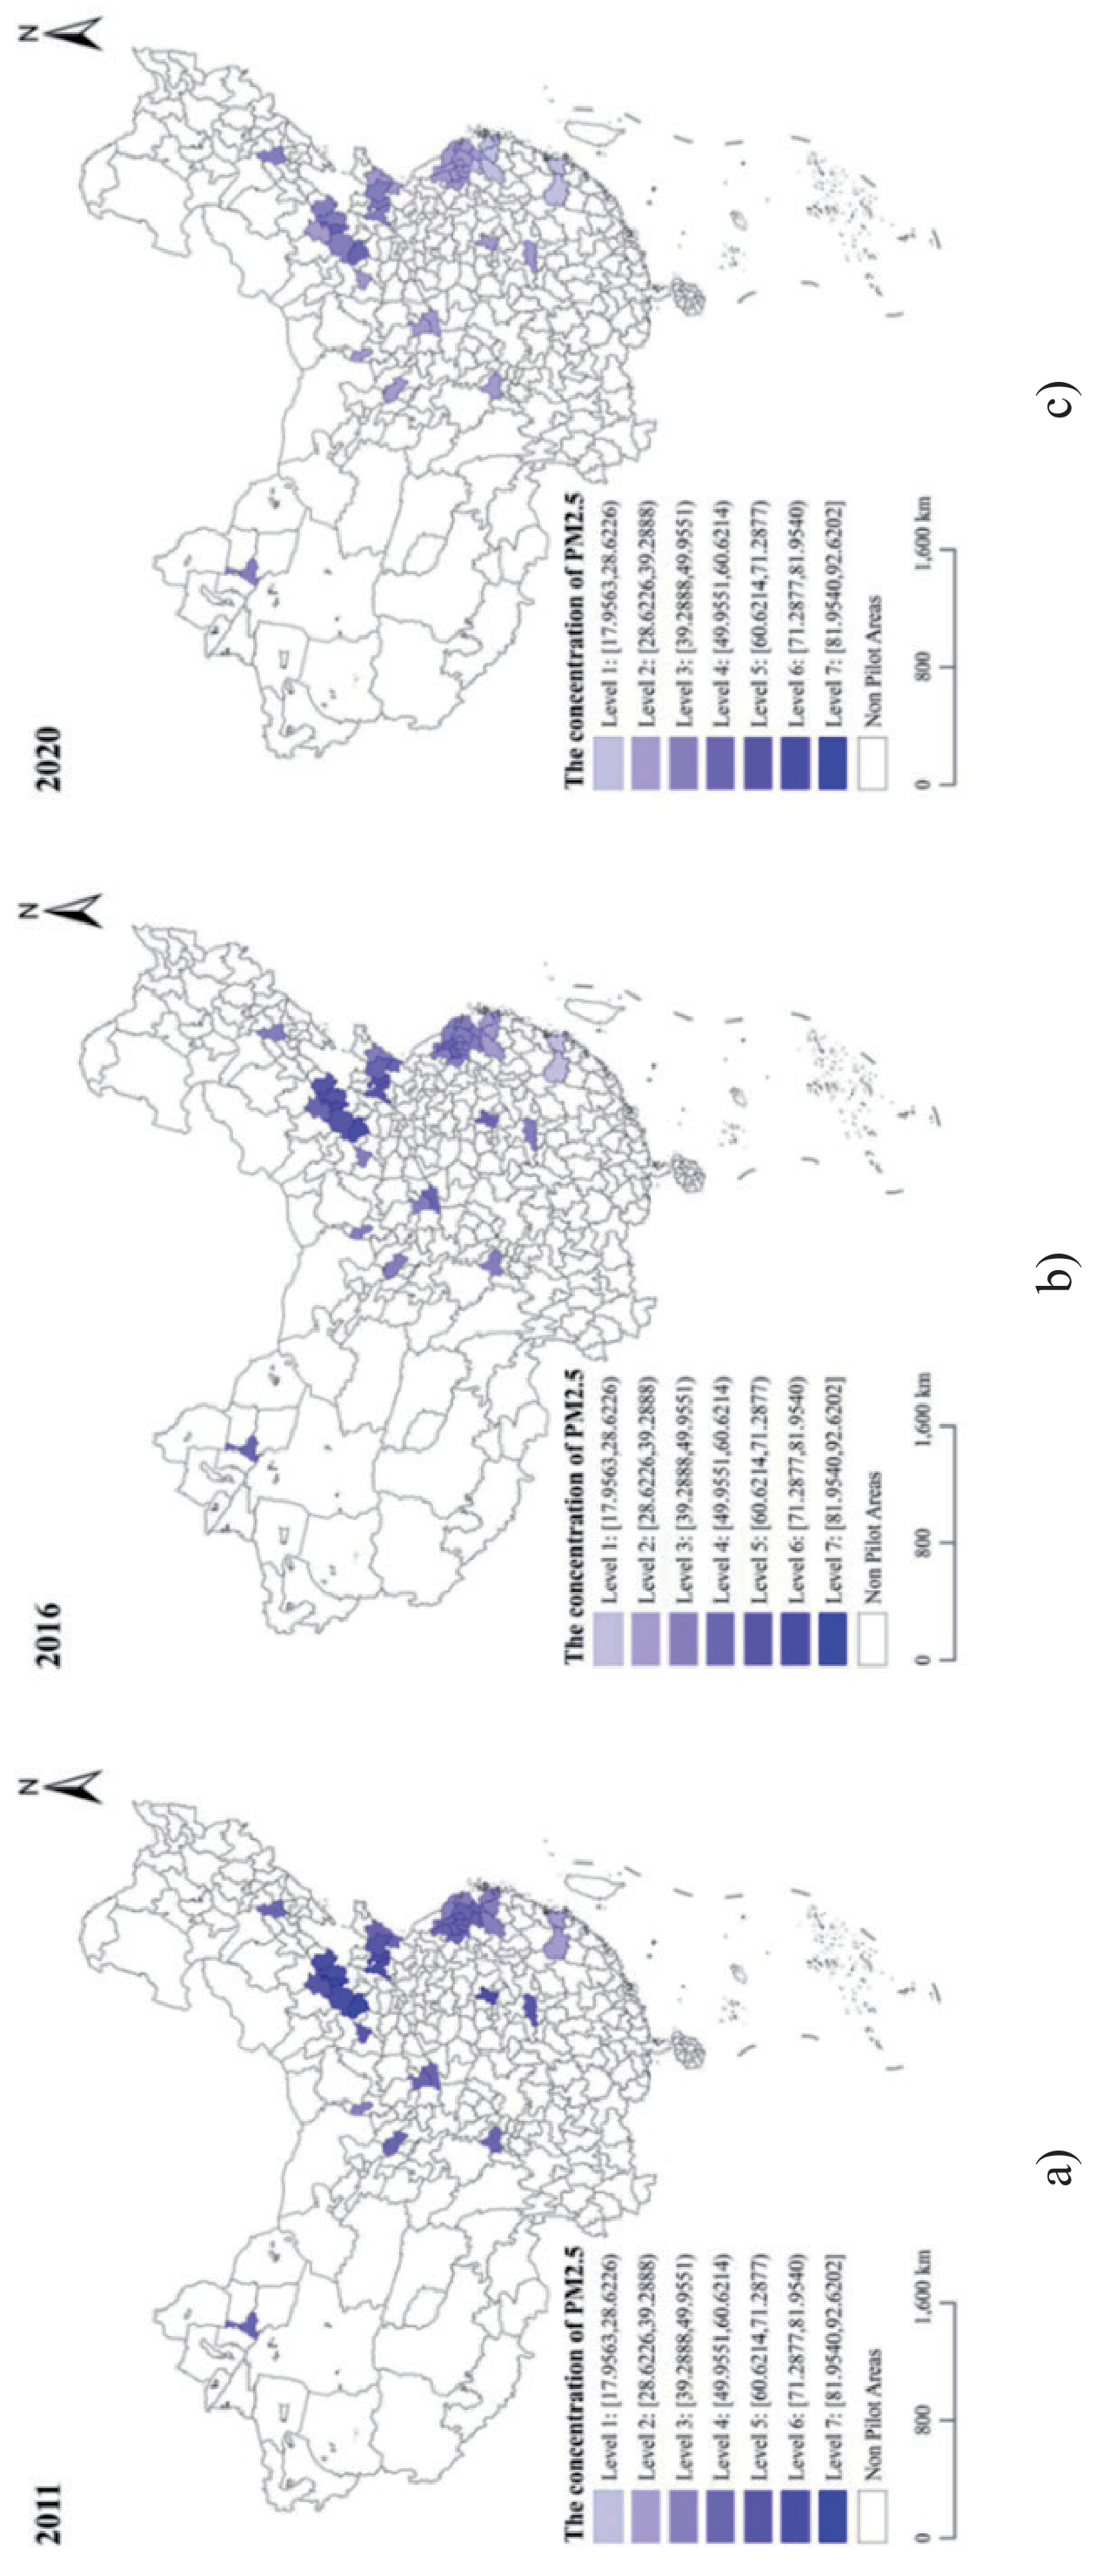
PM2.5, recognized as a major air pollutant, poses significant risks to public health due to its capability to infiltrate deep into the alveoli and subsequently enter the bloodstream [76]. PM2.5 originates from a variety of sources, including industrial emissions, vehicular exhaust, and natural events, and it has the propensity to persist in the atmosphere for prolonged periods, thereby facilitating the regional spread of pollution. Thus, the monitoring and regulation of PM2.5 concentrations are of paramount importance for improving air quality and safeguarding public health [76]. The findings of this study reveal a gradual decline in PM2.5 concentrations across China following the implementation of air pollution control policies between 2011 and 2020 (Fig. 1). Specifically, prior to the policy’s implementation in 2011, regions with elevated PM2.5 levels were primarily situated in northern and central China, particularly within the Beijing-Tianjin-Hebei region and the North China Plain, both of which experienced severe pollution. As the policy measures were progressively enforced, a noticeable reduction in PM2.5 concentrations began to manifest in certain northern regions by 2016, indicating the initial positive impacts of these interventions. Nevertheless, in heavily industrialized and densely populated areas, such as the Beijing-Tianjin-Hebei region, high pollution levels persisted, suggesting that the full benefits of the policies had not yet been realized. By 2020, further declines in PM2.5 concentrations were observed, marking a significant improvement in the efficacy of air pollution control policies, particularly in central and eastern regions where pollution levels were substantially mitigated, leading to a notable enhancement in overall air quality.
Robustness Tests
Parallel Trend Test
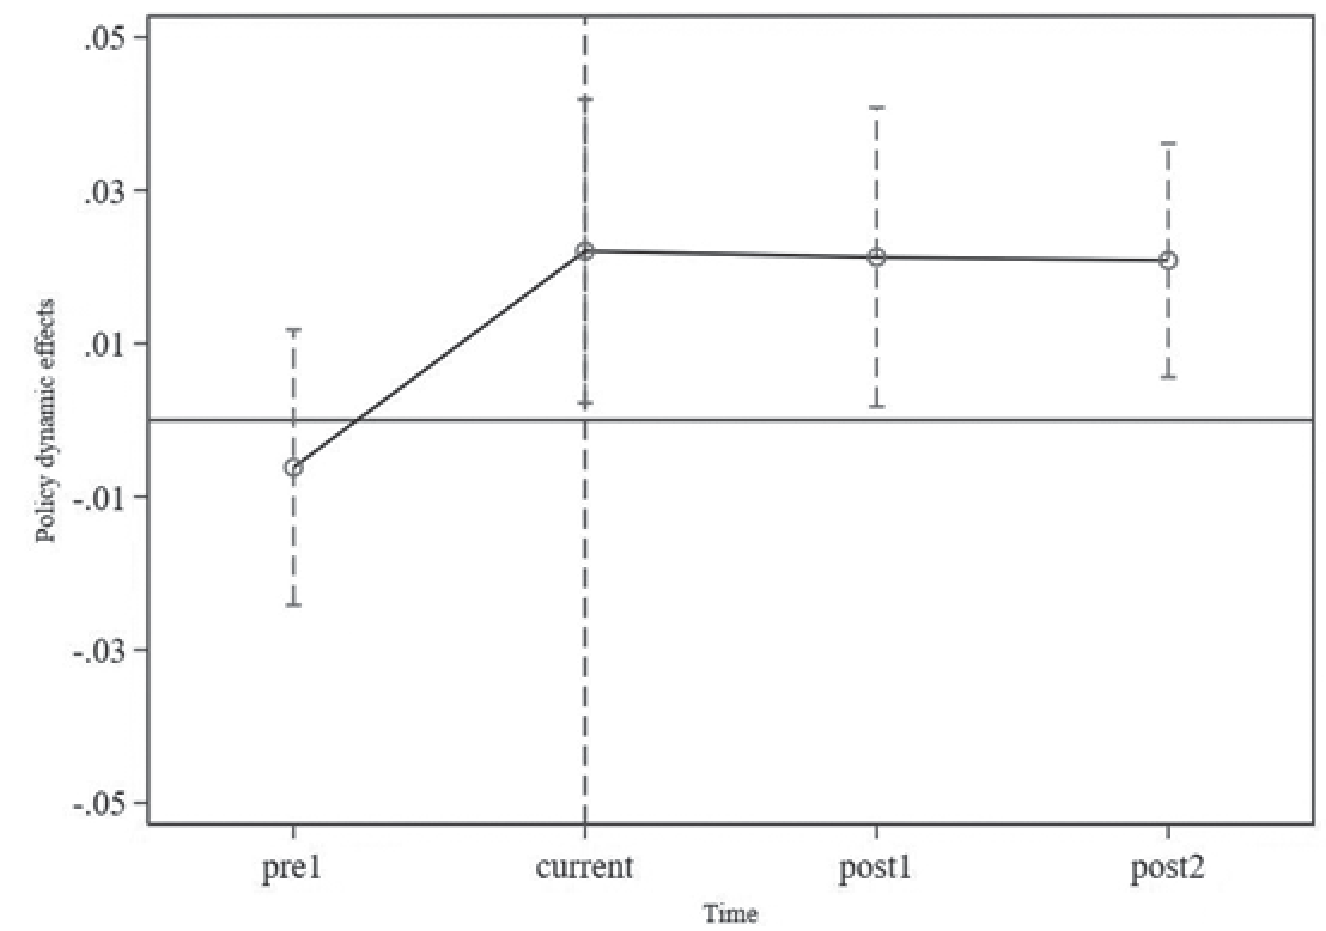
The parallel trend assumption is critical for applying DID modeling to evaluate policy effects. This assumption necessitates that, prior to the policy intervention, the core explanatory variables in both the pilot and non-pilot regions exhibit similar trends. To verify this assumption, the policy’s initial implementation year was designated as the baseline. We then examined the policy’s effects one year prior to and two years after its implementation. As depicted in Fig. 2, the trends for the pilot and non-pilot regions did not diverge significantly before the air pollution control policy was introduced, thereby satisfying the parallel trend assumption.
Placebo Trials to Exclude Randomized Outcomes
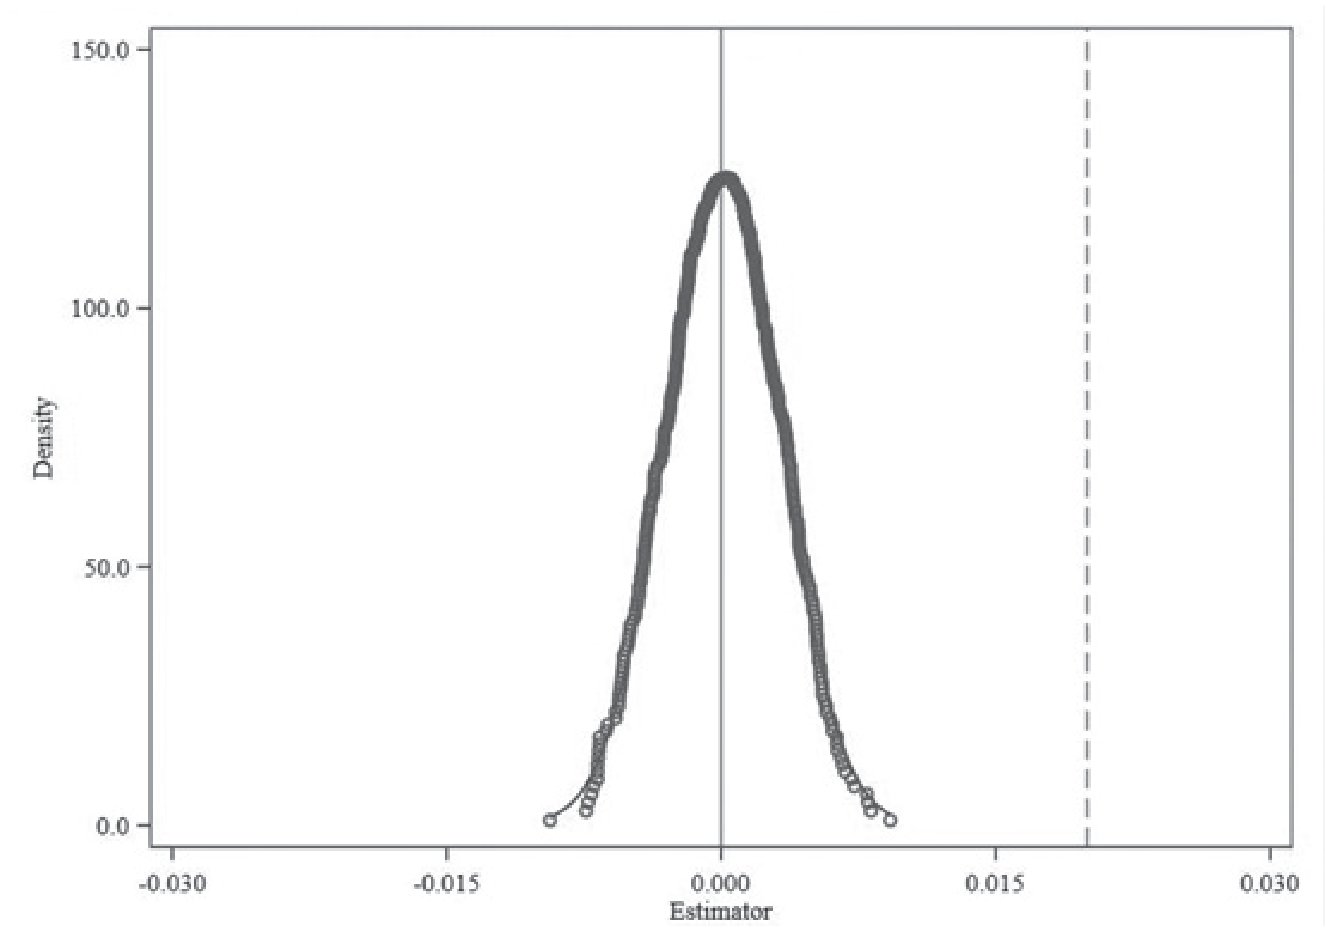
A placebo trial was conducted to ensure that random factors do not influence the observed results. The years and regions where air pollution control policies were implemented were randomized, following the methodology outlined by Chetty et al. [61]. This process was repeated 500 times; the outcomes are depicted in Fig. 3. The distribution of regression coefficients obtained from the randomization simulation approximates zero, and the coefficients from the benchmark regression remain entirely independent of this distribution. This finding underscores that the empirical results observed in this study are not the product of random outcomes.
PSM-DID
To address potential self-selection bias, this study employs the Propensity Score Matching Difference-in-Differences (PSM-DID) model as a robustness check to verify the validity of the regression results. The PSM-DID approach combines propensity score matching (PSM) and the Difference-in-Differences (DID) method, aiming to balance the treatment and control groups by ensuring they are comparable based on observed characteristics. In selecting matching variables, this study draws on established research and considers key demographic and socio-economic characteristics of the elderly population, including age, gender, educational attainment, marital status, health status, and household income, which are also used as control variables in the main regression. These variables were selected based on their relevance to the treatment assignment and potential influence on the outcomes of interest. A 1:1 nearest-neighbor matching technique without replacement was utilized to construct matched pairs, thereby ensuring a high level of comparability between treated and control groups [60].
By reducing observable differences between the two groups, this approach effectively mitigates concerns related to sample self-selection bias, leading to more reliable estimates in the DID model. As demonstrated in Table 4, the DID coefficient remains significantly negative, confirming the robustness and reliability of the primary regression results.
Table 4.
PSM-DID test results.
Heterogeneity Tests
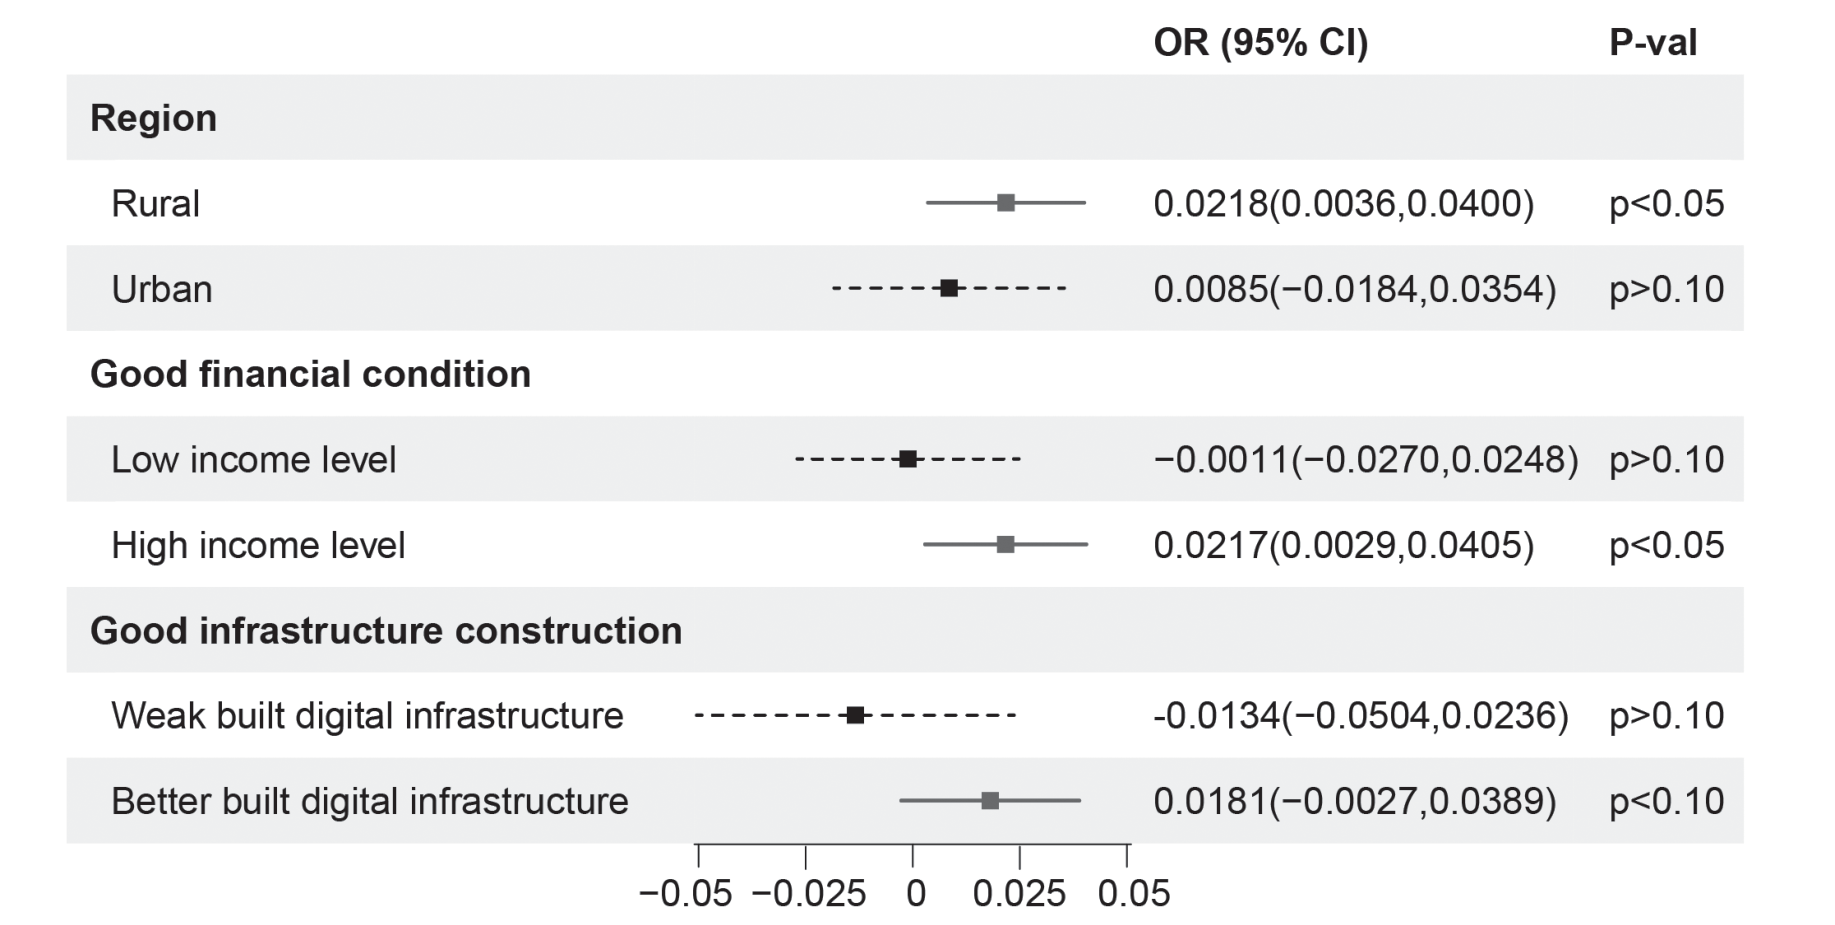
The heterogeneity analysis reveals that rural areas and high-income levels exhibit a significant positive association with the outcome (P<0.05), while urban areas, low-income levels, and weak digital infrastructure show no significant effects (P>0.10). Notably, better digital infrastructure demonstrates a near-significant effect (P<0.10). These findings are visually summarized in a forest plot, where solid red lines represent significant results, and dashed black lines indicate non-significant findings (see Fig. 4). The confidence intervals further illustrate the range of effects for each condition.
Pilot Region
Air pollution in rural areas is exacerbated by pollution transmission from urban regions, the relocation of polluting industries, and local sources [77]. These disparities arise from differences in governance, infrastructure, and lifestyles between urban and rural areas.
Rural areas face weaker environmental governance, with less stringent regulations than urban centers. While cities reduce emissions through stricter controls and enforcement, rural regions often host industries relocating to evade urban restrictions, worsening local air quality and exposing residents to greater health risks. Moreover, rural areas lack the advanced infrastructure of urban regions, such as comprehensive air pollution monitoring, accessible healthcare, and efficient public transportation. For instance, urban systems reduce vehicle emissions, whereas rural households often rely on biomass fuels for cooking and heating, further aggravating pollution.
Lifestyle and occupational differences intensify these disparities. Urban residents benefit from controlled indoor environments, while rural populations engage in outdoor activities, increasing pollutant exposure. Traditional heating methods like burning coal or wood further elevate indoor and ambient pollution in rural households.
Empirical findings highlight these challenges. Regression results show that air pollution prevention policies have had a more significant positive impact on the health of rural elderly populations, with a coefficient of 0.0218 significant at the 5% level, as depicted in Table 5. This suggests that rural populations, starting from a baseline of higher pollution exposure, gain more from systemic improvements.
In conclusion, weaker governance, limited infrastructure, and exposure-prone lifestyles make rural populations particularly vulnerable to air pollution. Addressing these challenges requires targeted interventions, such as subsidizing cleaner energy, improving rural healthcare access, and strengthening digital infrastructure for pollution monitoring. These measures are essential for reducing disparities and ensuring equitable health outcomes.
Economic Circumstances
The root cause theory of health posits [78] that socio-economic status constitutes a fundamental determinant of health disparities and inequalities [79]. Favorable economic conditions enhance the ability of older adults to maintain their health by leveraging external resources when faced with health risks. This study investigates whether the impact of air pollution control policies on the health of the elderly varies across different household income levels, categorizing participants into low-income and high-income groups based on the mean total household income among the elderly in the survey. As delineated in Table 6, the regression results indicate that the coefficient for the elderly with lower economic status is -0.0011 and does not achieve significance at the 10% confidence level. Conversely, the coefficient for the elderly with higher economic status is 0.0217. It is statistically significant at the 5% confidence level, highlighting that elderly individuals with higher economic status benefit more significantly from air pollution control policies, likely due to their greater access to resources for mitigating health risks associated with air pollution.
Digital Infrastructure
Establishing and developing robust digital infrastructure plays a pivotal role in effectively preventing and controlling pollution, contributing significantly to pollution monitoring and management efforts [80, 81]. Consequently, it is hypothesized that the impact of air pollution control policies on the health of the elderly might vary depending on the regional digital infrastructure development level. Various indicators of digital infrastructure—such as regional fiber optic cable density, per capita internet broadband access ports, and the percentage of relevant employees—were utilized to construct a composite index representing the level of digital infrastructure, employing the entropy weighting method. The regression analyses presented in Table 7 reveal that the coefficient for the elderly in regions with underdeveloped digital infrastructure is -0.0134 and does not reach significance at the 10% confidence level. In contrast, the coefficient for the elderly in regions with well-developed digital infrastructure is 0.0181. It is significant at the 10% confidence level, indicating that the policy effects are notably more pronounced in regions with advanced digital infrastructure, underscoring the critical role of technology in enhancing policy implementation, monitoring, and disseminating air quality information.
Mediating Effect
The results from the benchmark regression underscore that air pollution joint prevention and control policies exert a significantly positive impact on the health status of the elderly. To extend the analysis, this study explores the underlying mechanisms driving this relationship through theoretical inquiry. A considerable body of literature has established [82, 83] that improvements in air quality are closely associated with reductions in both the incidence and severity of acute and chronic illnesses—such as cardiovascular and respiratory diseases, as well as cancer—alongside a decrease in related mortality rates. Furthermore, air pollutants, particularly fine particulate matter like PM2.5, have been shown to negatively influence health-promoting behaviors [84, 85] and are linked to the onset of mental health issues such as depression, anxiety, and other adverse emotional states in the elderly. Given that the elderly are particularly susceptible to external environmental stimuli that may provoke respiratory conditions due to their declining physiological functions and compromised immune systems, the health risks posed by air pollution are considerable. Additionally, exposure to air pollutants can adversely affect the central nervous system through pathways involving inflammation and oxidative stress [86], impacting olfactory receptor neurons, the trigeminal nerve, or systemic circulation, thereby affecting the overall health of older adults. Accordingly, this study delves into the mechanisms by which air pollution joint prevention and control policies influence the health of the elderly, with a specific focus on the mediating effects at play.
Table 5.
Heterogeneity of region.
Improving Residential Air Quality
Drawing on existing literature, this study identifies the air quality of elderly residents’ homes as a mediating variable to examine the effects of coordinated regional air pollution control on their residential air quality. The regression results presented in Table 8 demonstrate that coordinated regional air pollution management policies significantly reduce the concentration of pollutants, such as PM2.5, in the air surrounding the elderly’s residences, thereby decreasing their exposure to harmful substances.
Respiratory Diseases
The empirical evidence underscores that joint air pollution prevention and control policies significantly contribute to elderly health by improving residential air quality and reducing the prevalence of respiratory diseases, such as lung diseases and asthma. These mechanisms provide robust support for the overall policy impact. The coefficients from the regression results in Columns (1) and (2) of Table 9 are statistically significant at the 5% and 1% levels, respectively, indicating that coordinated efforts in managing air pollution contribute positively to the health status of the elderly by decreasing the prevalence of lung diseases and asthma.
Discussion
The empirical results highlight the significant positive effects of coordinated air pollution prevention and control policies on elderly health. These effects are particularly evident in rural areas, among higher-income groups, and in regions with well-developed digital infrastructure. Moreover, the mechanisms reveal that improvements in residential air quality and reductions in respiratory diseases are crucial in achieving these outcomes. Building on these findings, the discussion section delves deeper into the implications of these results.
Discussion of Baseline Regression Results
The findings derived from the baseline regression analysis indicate that air pollution joint prevention and control policies significantly enhance the overall health of the elderly population. A plausible explanatory mechanism underlying these findings is that air pollution control policies contribute to improved health by reducing exposure to pollutants, particularly fine particulate matter (PM2.5), which is known to penetrate deep into the lungs and enter the bloodstream, increasing the risk of cardiovascular and respiratory diseases [87]. Implementing these policies leads to a marked reduction in PM2.5 concentrations, effectively decreasing the likelihood of older individuals inhaling hazardous substances [88].
Moreover, the World Health Organization (WHO) has emphasized that approximately 37% of premature deaths related to outdoor air pollution are attributable to ischemic heart disease and stroke, with an additional 18% and 23% linked to chronic obstructive pulmonary disease (COPD) and acute lower respiratory infections (ARIs), respectively [89]. Furthermore, 11% of these deaths were associated with respiratory cancers. The reduction in air pollution through policy implementation can, therefore, mitigate the incidence of lung diseases, asthma, and other respiratory conditions among the elderly, thereby enhancing their physical health and increasing their resilience to adverse environmental stimuli.
Table 6.
Heterogeneity between with or without good financial condition.
Discussion of Heterogeneity Results
Discussion of Regional Heterogeneity Effects
The heterogeneity analysis indicates a stronger impact of regional air pollution joint prevention and control policies on the health of rural elderly individuals, as elucidated in Table 3, whereas the effects on urban elderly individuals do not reach statistical significance. Before introducing these policies, polluting industries frequently relocated from strictly regulated urban areas to less regulated rural regions, exacerbating environmental pollution in these rural areas and heightening the health risks faced by the elderly population [90]. However, when implementing coordinated management policies, environmental regulations have been strengthened across all regions, effectively curbing the uncontrolled migration of polluting industries. As a result, the environmental quality in rural areas has witnessed substantial improvement, significantly enhancing the health status of the elderly population residing there [62]. In contrast, urban elderly individuals, who typically reside in areas with superior infrastructure and more stringent environmental protection measures, have experienced relatively less exposure to air pollution [91], resulting in negligible improvements in their health status following the policy’s implementation.
Table 7.
Heterogeneity between with or without good infrastructure construction.
Discussion of Heterogeneous Effects of Household Income
The analysis of heterogeneous effects, as depicted in Table 5, indicates that the impact of regional air pollution joint prevention and control policies on the health of elderly individuals with higher household incomes is more significant, while the effects on those with lower incomes do not achieve statistical significance. This disparity likely arises from wealthier individuals being better equipped to mitigate air pollution’s health impacts through protective measures before the policy’s implementation, such as using air purifiers, thereby maintaining their health status post-implementation. Research has demonstrated that individuals with higher incomes tend to possess greater coping capacity and resources, enabling them to adopt precautionary measures in response to environmental pollution, thus resulting in less long-term health damage [92]. Conversely, elderly individuals with lower incomes often lack the financial means to implement effective protective measures during periods of severe pollution, leading to irreversible health damage due to prolonged exposure to polluted environments. It has been observed that the deterioration in health among low-income individuals exposed to high levels of air pollution over extended periods is challenging to fully reverse through short-term policy improvements [93]. Accordingly, even with improved air quality following policy implementation, the health status of low-income elderly individuals remains difficult to enhance significantly due to pre-existing health damage [94]. This observation clarifies why the health impacts of regional air pollution prevention and control policies are more pronounced among high-income older adults, whereas the effects on low-income older adults are relatively limited.
Discussion of Heterogeneous Effects of Regional Information Infrastructure Development
The analysis of heterogeneous effects, as delineated in Table 6 and illustrated in Fig. 3, demonstrates that the impact of regional air pollution joint prevention and control policies on the health of the elderly is more pronounced in regions with well-developed digital infrastructure. In contrast, the effects in regions with underdeveloped digital infrastructure do not reach statistical significance. This phenomenon may be attributed to regions with robust digital infrastructure providing the elderly with easier access to real-time information and early warnings [95] related to air pollution, enabling them to take timely protective measures, such as reducing outdoor activities or utilizing air purifiers. Moreover, well-developed digital infrastructure enhances governmental monitoring and oversight of pollution sources, facilitating the more effective implementation of regional air pollution prevention and control policies [96] and improving residents’ living environment. This efficient regulatory framework leads to a more substantial improvement in air quality in areas with strong digital infrastructure, thereby exerting a more significant protective effect on the health of the local elderly population [97]. Conversely, regions with underdeveloped digital infrastructure experience delays in information dissemination and limited pollution regulatory capacity, hindering the government’s effective control and management of pollution sources. Hence, older individuals in these areas may be unable to take necessary countermeasures in a timely manner, resulting in prolonged exposure to polluted environments and potentially irreversible health damage. Previous studies have indicated that even after implementing policies in these regions, the lack of infrastructure has resulted in limited policy effectiveness and minimal improvements in the health status of the elderly [98]. Therefore, enhanced digital infrastructure not only improves their capacity to cope with air pollution but also increases the efficiency of environmental regulation, thereby amplifying the impact of regional air pollution prevention and control policies on the health of older individuals in these areas. In contrast, the limited impact of policies in regions with weak digital infrastructure constrains the potential improvements in the health of older adults.
Table 9.
Results of mediating effect.
Conclusions
Drawing on multi-period data from CHARLS, this research has thoroughly explored the impact of air pollution joint prevention and control policies on the health status of the elderly. The study’s findings are summarized as follows:
(1) This study demonstrates that implementing coordinated air pollution prevention and control policies significantly enhances the overall health of elderly populations, particularly in improving physiological and mental health outcomes. This conclusion is substantiated by rigorous analyses, including parallel trend tests, placebo tests, and propensity score matching (PSM), which consistently affirm the robustness of the results.
(2) The findings reveal pronounced heterogeneity in policy effects. Rural elderly individuals, those with higher economic status, and residents of regions with advanced digital infrastructure benefited the most from these policies.
(3) The mechanisms underlying these improvements are primarily attributed to better air quality, reflected in reduced PM2.5 levels and a decrease in respiratory diseases such as asthma and chronic lung conditions. These findings provide strong empirical evidence, underscoring the importance of further exploring the effects of such policies on the health of the elderly population.
Policy Recommendations
The discussion highlights the critical factors influencing the success of air pollution control policies, such as regional disparities, economic conditions, and technological infrastructure. These insights underscore the necessity of developing targeted and inclusive policy measures to ensure equitable and effective outcomes. Building on the empirical evidence and discussions, this section outlines actionable policy recommendations to enhance the effectiveness of air pollution prevention and control strategies, particularly in addressing health disparities among the elderly.
(1) Clarifying Policy Priorities. In the short term, establishing real-time air quality monitoring systems in high-risk regions and implementing stricter PM2.5 emission standards in areas with high elderly population densities should be the primary focus. Mid- to long-term goals should include transitioning industries toward green technologies and strengthening public awareness campaigns on air pollution prevention, with a particular emphasis on protecting elderly health. These priorities will guide the implementation process, ensuring that immediate actions are taken to address the most pressing issues while also setting the stage for sustained improvements in the long run.
(2) Active implementation and health promotion innovations. It is essential to actively pursue implementing air pollution joint prevention and control policies while simultaneously innovating new health promotion models specifically designed for the elderly. This process should involve a clear delineation of the health risks associated with air pollution and a comprehensive explanation of the underlying mechanisms. Establishing air quality standards tailored to the needs of elderly individuals, such as stricter PM2.5 limits in regions with a high density of elderly populations, is essential. Regular reviews and adjustments of these standards based on real-time pollution data should also be incorporated alongside establishing a long-term, effective system for monitoring, early warning, and evaluation. Continuously tracking the effects of policy implementation will allow for timely adjustments and optimizations of health promotion strategies for the elderly. Moreover, public awareness campaigns should be designed to convey the hazards of air pollution in an accessible and compelling manner, thereby enhancing the elderly’s capacity for self-protection and their ability to manage health risks effectively.
(3) Enhancing information infrastructure by incorporating advanced technologies like IoT and AI can enable real-time air quality monitoring and personalized health warnings for elderly individuals in high-risk areas. The integration of next-generation information technologies, such as the Internet of Things, artificial intelligence, cloud computing, and big data, has the potential to significantly enhance air pollution governance. This includes the development and deployment of advanced air pollution detection equipment, as well as the cultivation of a workforce skilled in air pollution monitoring and regulatory practices. Improving information management systems, dismantling communication barriers between various departments, and increasing the overall efficiency of air pollution governance efforts are also essential components of this strategy.
(4) Creating a coordinated governance model. In urban areas, focus on reducing industrial emissions and implementing stricter vehicle emissions standards. In rural areas, prioritize promoting clean energy solutions, such as subsidizing electric cooking and heating equipment and enhancing public education on air pollution prevention. This model should adapt to local conditions and leverage the respective strengths of both urban and rural governance structures. Clearly delineating the responsibilities related to air pollution control is necessary to ensure that the health rights of both urban and rural residents are protected equitably. In urban areas, a focused effort should be made to promote energy conservation and emission reduction while also encouraging enterprises to adopt environmentally compliant operational practices. In rural areas, it is crucial to elevate residents’ environmental awareness, discourage environmentally harmful practices such as centralized straw burning, promote the adoption of clean energy, and enhance the management of pollution sources stemming from agricultural vehicles and small enterprises.
(5) Addressing income disparities and technical barriers. Addressing income disparities and dismantling technical barriers that hinder effective air pollution management is vital. Enhancing social and financial incentive mechanisms and providing targeted subsidies can encourage enterprises to innovate and adopt environmentally friendly practices. Introduce targeted financial assistance programs for low-income elderly individuals, such as subsidies for purchasing air purifiers or installing air filtration systems, and ensure free respiratory health screenings in high-pollution areas. Controlling research and development costs could help reduce the market prices of air purifiers and related equipment. Additionally, establishing compensation standards for economically disadvantaged elderly individuals, increasing medical subsidies, ensuring comprehensive access to basic medical services, and promoting equitable self-care capabilities for older adults are essential measures that should be prioritized.
(6) Drawing on successful international experiences can provide valuable insights for improving domestic air pollution control policies. For instance, the European Union’s transboundary air pollution agreements offer a model for cross-regional cooperation in air quality management, where neighboring countries collaborate to monitor, share air quality data, and enforce emission reduction targets. Similarly, the United States’ Clean Air Act, which has been effective in reducing industrial emissions, provides a framework that can be adapted to local conditions in China. Additionally, Japan’s use of advanced air quality monitoring systems and public health awareness campaigns serves as an exemplary model for integrating technology with public health protection. These international examples demonstrate the effectiveness of coordinated efforts, stringent regulations, and public engagement can be adapted to China’s unique environmental and demographic challenges.
Limitations
While this study offers valuable insights, several limitations should be acknowledged. First, despite controlling for demographic and regional variables, additional confounding factors may be unaccounted for, which could influence the health outcomes of the elderly. Second, the reliance on self-reported health and mental health data may introduce biases, as these reports might not fully align with the actual health conditions of the respondents. Third, the analysis of the mediating effects of coordinated air pollution control policies on the health of older adults focused solely on changes in PM2.5 concentrations, thereby overlooking other significant air pollutants. Lastly, the heterogeneity analysis, particularly concerning urban-rural differences, was constrained by data availability, limiting the depth of exploration into the underlying causes of these disparities. Future research should aim to address these limitations comprehensively, enhancing the overall understanding of the complex interactions between air pollution policies and the health of the elderly population.
To address the limitations outlined, future research should focus on exploring additional confounding factors and integrating more diverse data sources to improve the robustness of findings. Efforts should also include using objective health measures to complement self-reported data, expanding the analysis to other air pollutants beyond PM2.5, and conducting in-depth investigations into urban-rural disparities. These steps will help provide a more comprehensive understanding of the interactions between air pollution policies and elderly health, offering valuable insights for developing more targeted and effective interventions.

